
Does Estrogen Deficiency Shrink Breast Size? Medical Truth

Does hormonal decline cause breasts to shrink? Dropping estrogen levels directly trigger lobular involution of breast glandular tissue, resulting in diminished glandular density, lax supportive ligaments, and noticeable breast deflation and sagging. However, recovery requires a personalized medical protocol combined with safe clinical screening; never self-supplement hormones without a specialist's prescription.
1. Anatomical Decoding: How Hormones Shape Breast Size and Firmness
Many women mistakenly assume breasts are composed purely of fat. In reality, from a clinical anatomy perspective, the female breast is a sophisticated complex structure consisting of three primary components: Glandular tissue (lobules and ductal network), surrounding adipose tissue, and the suspensory Cooper's ligaments anchoring the entire breast mass to the pectoralis major muscle.
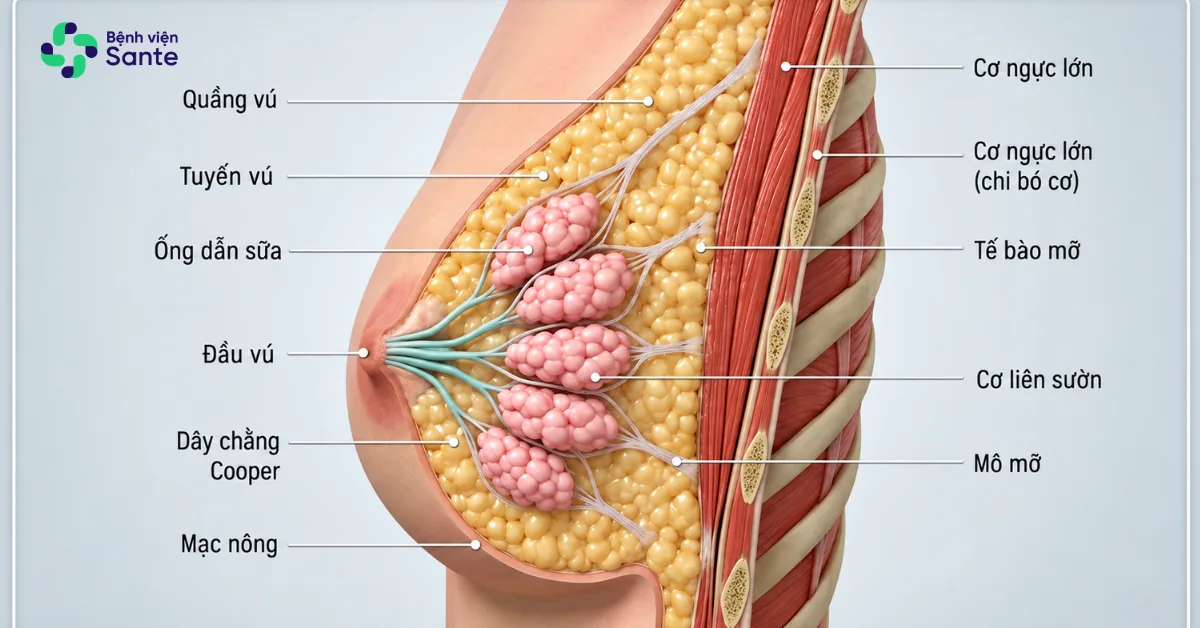
Breasts are not an immutable mechanical mass. On the contrary, they represent one of the most sensitive target organs to female sex hormone fluctuations:
The Golden Duo Estrogen - Progesterone and the Glandular Network
- Estrogen: Acts as the "master architect," stimulating ductal branching, enhancing microvascular circulation to nourish breast tissue, and activating local adipose accumulation receptors, creating fullness and feminine softness.
- Progesterone: Promotes full development of secretory lobules, imparting taut roundness and structural firmness to breast segments.
Cooper's Ligaments: The Load-Bearing Framework of the Breast
Cooper's ligaments are resilient fibrous connective tissue bands that define breast contour against gravitational pull. To maintain supple elasticity, the collagen network within Cooper's ligaments relies heavily on stable estrogen levels. When this hormone is abundant, breasts preserve natural projection and elevation.
2. Does Hormonal Decline Truly Shrink Breasts? The Mechanism of Lobular Involution
The answer from medical specialists is: YES. When the body experiences estrogen deficiency or dysregulation, breasts undergo biological involution, resulting in tissue atrophy and loss of real volume.
The pathogenesis unfolds across three common clinical scenarios:
Postpartum and Weaning: Deflated Breasts and Glandular Atrophy
During pregnancy and lactation, surging prolactin and estrogen stimulate glandular alveoli to maximum distension. However, upon weaning, the abrupt plummet of lactogenic hormones alongside estrogen fluctuations precipitates acute glandular retraction. Consequently, breast glandular tissue atrophies rapidly while the cutaneous envelope remains overstretched, producing an empty upper pole and pronounced ptosis.
Perimenopause and Menopause: When Estrogen Drops Drastically
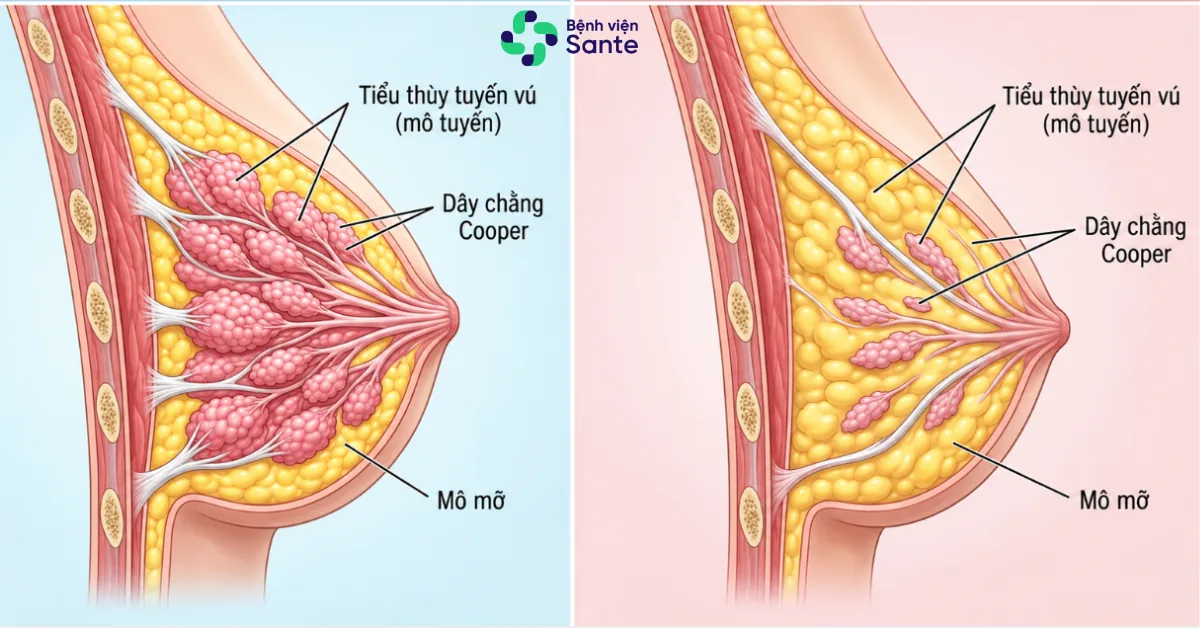
Entering ages 40–50, ovarian function declines markedly. Plummeting estrogen levels induce the medical condition known as Lobular Involution:
- Secretory lobular units gradually regress and vanish.
- Collagen-rich stroma degenerates, replaced by loose, less cohesive adipose tissue.
- The breast loses its internal structural core, becoming soft, deflated, and visibly reduced in physical volume.
Hormonal Imbalance in Young Women: PCOS and Exhaustion
Not only older women, but many young females with hypothalamus-pituitary-ovarian axis dysregulation, chronic stress-induced estrogen deficiency, irregular menses, or polycystic ovary syndrome (PCOS) observe underdeveloped breasts and premature breast volume loss during their peak reproductive years.
3. Other Common Causes of Breast Shrinkage Beyond Hormonal Factors
Although sex hormones play a pivotal role, not all cases of breast shrinkage stem from endocrine decline. Prematurely attributing volume loss solely to hormones while ignoring lifestyle or pathological factors risks adopting misaligned therapies:
- Sudden weight loss from crash dieting: Adipose tissue accounts for 50–70% of breast volume depending on constitution. When weight drops too rapidly (cutting carbohydrates, improper intermittent fasting), the body catabolizes systemic fat—typically mobilizing breast and facial reserves first—deflating the bust despite normal hormone levels.
- Supportive matrix breakdown from biological aging: Over time, progressive cleavage of collagen and elastin fibers elongates Cooper's ligaments. Breasts sag toward the abdominal wall, creating an illusion of severe volume loss by flattening the upper chest.
- Wearing ill-fitting bras or chronic compression: Constrictive bras impair microcirculation and lymphatic drainage nourishing breast tissue; conversely, lack of support during vigorous workouts tears internal suspensory bundles.
- Chronic neurogenic stress and sleep deprivation: Prolonged hypercortisolemia dampens gonadotropic signaling, deranging protein anabolism and expediting early adipocyte degradation in breast cushions.
4. Clinical Comparison: Breast Shrinkage from Hormonal Decline vs. Weight Loss / Mechanical Aging
| Comparison Criteria | Shrinkage from Hormonal Decline | Shrinkage from Rapid Weight Loss | Sagging from Mechanical Aging |
|---|---|---|---|
| Primary Deficit Site | Glandular lobules regress, upper pole deflates, breast loses cohesive firmness. | Loss of surrounding adipose mantle; underlying glandular parenchyma retains density. | Cooper's ligaments slacken; glandular mass descends below the inframammary fold. |
| Associated Systemic Signs | Oligomenorrhea/amenorrhea, hot flashes, xerosis, hypoactive libido, emotional lability. | Marked weight loss, telogen effluvium, sarcopenia, xerosis from caloric deficit. | Periorbital rhytids, solar lentigines, dermatochalasis on arms, neck, and thighs. |
| Prevalent Age Group | Post-weaning mothers, perimenopausal females (40–52 years), or premature ovarian insufficiency. | Any age group (preponderant in young females undergoing strict dieting or overtraining). | Females aged 35+, multiparous women, or individuals engaged in heavy physical labor. |
| Spontaneous Reversibility | Difficult to spontaneously reverse if glandular acini have fibrosed into involuted fat. | Reversible upon restoring a balanced caloric and macronutrient regimen. | Irreversible naturally due to permanent mechanical slackening of Cooper's ligaments. |
5. Can Shrunk Breasts Recover Naturally Once Hormones Stabilize?
The restorative potential of breast volume depends on timing of intervention and structural extent of tissue involution of breast tissue:
- Functional endocrine fluctuation phase: If volume drops from transient stress, malnutrition, or brief menstrual irregularities, optimizing lifestyle, healthy nutrition (quality protein, Omega-3s, vitamin E, zinc), and circadian rhythm can partially restore breast fullness.
- Irreversible structural involution phase: For multiparous females with empty glandular parenchyma, or postmenopausal women with fibrosed lobules and mechanically stretched Cooper's ligaments, hormone rebalancing alone cannot spontaneously retract or expand breast contours back to pre-pregnancy states through conventional natural means.
Frequently Asked Questions About Hormonal Decline and Breast Size
1. Is postmenopausal breast shrinkage and sagging a sign of breast cancer?
No. This is normal physiological lobular involution resulting from ovarian cessation of estrogen secretion. However, if shrinkage is accompanied by abnormal signs such as palpable hard nodules, nipple retraction, bloody nipple discharge, or peau d'orange skin texture, visit a specialized hospital immediately for digital mammography screening.
2. Can drinking soy isoflavones restore breast size after weaning?
Impossible. Soy germ extracts provide plant phytoestrogens with very weak bioactivity (1/1,000 to 1/100,000 of endogenous human estrogen), incapable of restoring involuted glandular volume or tautening mechanically stretched Cooper's ligaments. High-dose overuse may also elevate the risk of breast cysts and uterine leiomyomas.
3. Can weightlifting reverse breast atrophy caused by hormonal decline?
Targeted gym workouts only hypertrophy the pectoralis major muscle underlying the breast, elevating the bust by approximately 1–2 cm, but cannot regenerate lost glandular parenchymal or adipose layers. Strenuous overtraining paired with rigid dieting may even accelerate breast fat depletion.
4. Does endoscopic breast augmentation at Sante Hospital interfere with future breast cancer screening?
Absolutely not. At Sante Hospital, endoscopic breast augmentation places the implant beneath the pectoralis major muscle (or via Dual Plane placement), ensuring total anatomical isolation from the overlying breast glandular tissue. Consequently, subsequent screening modalities such as breast ultrasound, digital mammography, or MRI capture 100% of natural glandular tissue without obstruction.
Breast Screening & Consultation for Bust Rejuvenation with Specialists
The specialist team in Obstetrics, Gynecology, and Aesthetic Plastic Surgery at Sante Hospital is always ready to accompany you, performing glandular ultrasound screening and advising safe, evidence-based breast rejuvenation solutions.

